
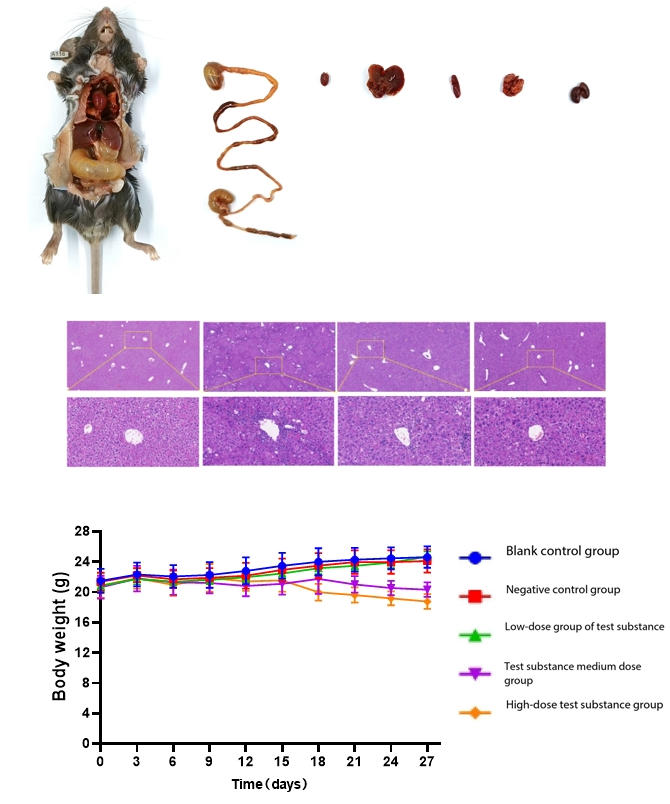
Why a head-to-head look matters now
Labs choosing cell-derived xenograft (CDX) models need clear trade-offs: speed, immune context, and reproducibility. This piece compares common CDX setups so you can match model choice to study goals without overpromising results. If you plan non-terminal exploratory work, consider contracting non-glp studies toxicology services for rapid turnaround and iterative dosing. Real-world experience from Boston contract labs shows that early, pragmatic model selection saves months on downstream pharmacodynamics and bioanalytical validation.
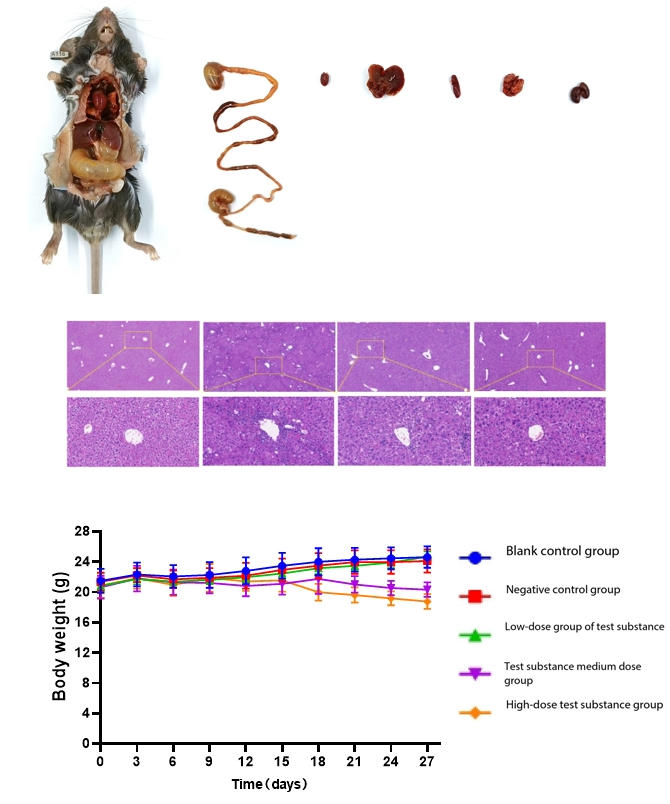
Core comparison criteria
Focus on three practical metrics when comparing CDX models: translational relevance, throughput, and data clarity. Translational relevance tracks how well tumor growth and drug response mimic clinical biology; throughput addresses cohort size and study length; data clarity covers endpoints like tumor volume, histopathology, and toxicokinetics. Models with engineered immune components can hint at immune interactions but add variability. A simple flank CDX gives clean tumor-volume curves fast. Use dose-ranging and route-of-administration decisions to control variability early.
Operational teardown: what labs commonly miss
Procedural details matter and often decide project success. Labs skip standardized sampling windows for toxicokinetics, or they lump histopathology scoring across inconsistent timepoints—those mistakes kill comparability. I’ve seen studies where bioanalytical methods weren’t locked before dosing; results were noisy and costly to salvage. In the operational production teardown we compare assay timing, tissue-processing SOPs, and terminal pathology windows and explicitly embed {main_keyword} and {variation_keyword} into run sheets to avoid ambiguity. Also weigh non-GLP options: using a non-glp toxicology study cro can speed iterative testing, but confirm sample storage rules and QA checkpoints up front.
Alternatives and the usual mistakes
Alternatives to CDX include patient-derived xenografts (PDX) and syngeneic models. PDX gives better clinical fidelity at the cost of throughput and higher variability; syngeneic models offer intact immunity but limit human-target testing. Common mistakes: mismatching endpoint assays to model type, skipping baseline biomarker panels, and underpowering groups for expected variability. Fix these by mapping each endpoint—imaging, histopathology, cytokine panels—to specific timepoints, then build cohorts that tolerate expected variance. A short pilot run for pharmacodynamics clarifies doses and reduces wasted animals.

Three golden rules for choosing the right non-GLP CRO
1) Define reproducible endpoints before contracting: spell out tumor measurement frequency, histopathology scoring method, and toxicokinetics sampling windows. Those parameters must be in the protocol, not scribbled notes. 2) Validate assay handoffs: confirm bioanalytical methods, sample storage temperatures, and turn-around reporting timelines. This prevents late surprises when data arrives. 3) Match CRO capacity to study rhythm: pick a partner that runs the cohort sizes and dose-escalation schemes you need, not the one with the lowest price. These three metrics—endpoint clarity, assay handoff integrity, and operational fit—separate productive CRO relationships from costly ones.
Closing assessment and next steps
Comparing CDX models is about matching constraints to questions: use fast flank models for dose-selection and larger cohorts for signal detection; pick PDX or immune-enabled systems when mechanism fidelity matters. The practical choices you make now shape downstream bioanalytical, toxicokinetics, and histopathology workloads. —Choosing a partner like Jennio reduces back-and-forth because they align study design with on-site capabilities and the sampling windows you need for clean, usable data. Jennio Biotech.